First EU gene therapy joint assessment: clinical effect confirmed, but Ireland does not recommend reimbursement at reported price
Published 15 September 2026
Last update 16 September 2026
236
On 7 September, the European Commission published the first Joint Clinical Assessment (JCA) of the gene therapy Itvisma (onasemnogene abeparvovec) for the treatment of spinal muscular atrophy in patients aged 2 years and older.
This is one of the first practical examples of the operation of the new HTA Regulation mechanism in the European Union.
 What the STEER Study Showed
The pivotal STEER study included 126 previously untreated patients aged 2 to 18 years who were able to sit independently but not walk.
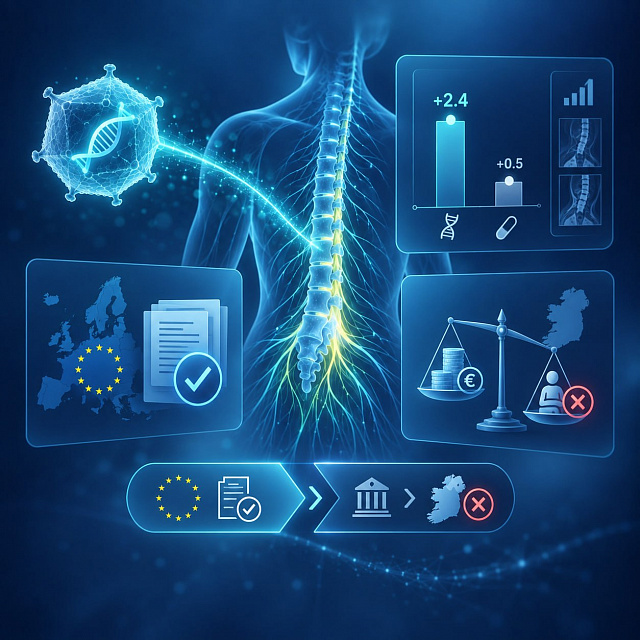
At 52 weeks, the mean change in motor function on the HFMSE scale was:
— +2.4 points with Itvisma
— +0.5 points in the sham-control group
However, for reimbursement decisions, what matters is not only the clinical effect itself, but also another question: how well is the advantage of the new gene therapy demonstrated compared with already available treatments for SMA?
 Where Uncertainty Remains
This is precisely where considerable uncertainty remains.
For comparisons with active alternatives, indirect methods of assessment had to be used. In addition, the registered population for Itvisma is broader than the population of the pivotal clinical trial.
This matters for national healthcare systems, which must make decisions not only about the clinical value of the drug, but also about price, reimbursement, and funding conditions.
 Ireland Has Already Used the JCA Results
It is particularly notable that Ireland has already used the results of the European JCA in its national assessment.
This became the first completed national assessment of a medicinal product using EU JCA.
Based on the results of a Rapid Review, the Irish National Centre for Pharmacoeconomics (NCPE) did not recommend Itvisma for reimbursement at the price proposed by the manufacturer. At the same time, conducting an additional full HTA was deemed unnecessary.
The final decision remains with the Health Service Executive (HSE).
 Why This Matters
This case clearly demonstrates that a single European clinical assessment does not mean automatic access to therapy.
JCA can reduce duplication of evidence assessment between countries, but issues of price, economic affordability, and funding remain national.
For orphan and gene technologies, this is particularly important: regulatory approval and demonstrated clinical effect are not sufficient if uncertainty remains regarding comparative efficacy and the price does not correspond to the value of the technology.
 Sources:
European Commission — Joint Clinical Assessment Report on onasemnogene abeparvovec (Itvisma), 7 September 2026
National Centre for Pharmacoeconomics, Ireland
This is one of the first practical examples of the operation of the new HTA Regulation mechanism in the European Union.
What the STEER Study ShowedThe pivotal STEER study included 126 previously untreated patients aged 2 to 18 years who were able to sit independently but not walk.
At 52 weeks, the mean change in motor function on the HFMSE scale was:
— +2.4 points with Itvisma
— +0.5 points in the sham-control group
However, for reimbursement decisions, what matters is not only the clinical effect itself, but also another question: how well is the advantage of the new gene therapy demonstrated compared with already available treatments for SMA?
Where Uncertainty RemainsThis is precisely where considerable uncertainty remains.
For comparisons with active alternatives, indirect methods of assessment had to be used. In addition, the registered population for Itvisma is broader than the population of the pivotal clinical trial.
This matters for national healthcare systems, which must make decisions not only about the clinical value of the drug, but also about price, reimbursement, and funding conditions.
Ireland Has Already Used the JCA ResultsIt is particularly notable that Ireland has already used the results of the European JCA in its national assessment.
This became the first completed national assessment of a medicinal product using EU JCA.
Based on the results of a Rapid Review, the Irish National Centre for Pharmacoeconomics (NCPE) did not recommend Itvisma for reimbursement at the price proposed by the manufacturer. At the same time, conducting an additional full HTA was deemed unnecessary.
The final decision remains with the Health Service Executive (HSE).
Why This MattersThis case clearly demonstrates that a single European clinical assessment does not mean automatic access to therapy.
JCA can reduce duplication of evidence assessment between countries, but issues of price, economic affordability, and funding remain national.
For orphan and gene technologies, this is particularly important: regulatory approval and demonstrated clinical effect are not sufficient if uncertainty remains regarding comparative efficacy and the price does not correspond to the value of the technology.
Sources:European Commission — Joint Clinical Assessment Report on onasemnogene abeparvovec (Itvisma), 7 September 2026
National Centre for Pharmacoeconomics, Ireland